








In the intricate landscape of hematologic oncology, thrombotic complications are a recognized, albeit dreaded, hazard. Usually emerging in the crucible of active chemotherapy or trailing in the wake of central venous catheter placement, blood clots present a continuous clinical challenge. However, a recent case report published in Frontiers in Hematology (Volume 5, 2026) highlights a remarkably rare and diagnostically confounding clinical presentation: a large, asymptomatic right atrial thrombus discovered in a 21-year-old woman during her pre-treatment assessment for newly diagnosed classical Hodgkin lymphoma (cHL).
The patient, presenting with classic B-symptoms and localized lymphadenopathy, was found to have the intracardiac mass just 13 days after the placement of a peripherally inserted central catheter (PICC). This unexpected finding forced an immediate pivot in her clinical management, demanding advanced multimodality imaging to differentiate a benign or catheter-induced thrombus from direct tumor infiltration. Through a meticulously coordinated transition from low-molecular-weight heparin (LMWH) to targeted direct oral anticoagulant (DOAC) therapy—navigating complex pharmacological intersections with upcoming chemotherapy—the multidisciplinary team at Padua University Hospital successfully treated both the malignancy and the cardiovascular complication.
The case underscores a critical medical takeaway: intracardiac thrombosis, while exceedingly rare prior to systemic therapy in Hodgkin lymphoma, must remain high on the differential diagnosis list during initial staging work-ups. The rapid deployment of multimodality imaging and tailored anticoagulation can successfully neutralize these life-threatening events without interrupting life-saving cancer treatment protocols.
Detailed Chronology: From Presentation to Resolution
Clinical Presentation and Initial Work-Up
The patient’s journey began when she sought medical evaluation at the Hematology Unit of Padua University Hospital for a self-detected, painful laterocervical lymphadenopathy. Her clinical picture was compounded by classic, systemic symptoms of advanced lymphoproliferative disease: profuse night sweats, generalized pruritus, and an unintentional weight loss of 8 kilograms over the span of a single month.
Initial laboratory investigations revealed a striking inflammatory and hematologic response characterized by neutrophilic leukocytosis, mild anemia, and thrombocytosis. Specifically, her white blood cell count registered at $15.95 times 10^9/textL$ (with neutrophils at $11.50 times 10^9/textL$), hemoglobin at $104text g/L$, and platelets elevated at $548 times 10^9/textL$. Inflammatory markers were similarly pronounced, with an erythrocyte sedimentation rate (ESR) of $92text mm/h$, while lactate dehydrogenase (LDH) sat within normal limits at $185text U/L$.
A subsequent head and neck ultrasound revealed multiple enlarged, hypoechoic lymph nodes—the largest measuring between 2 and 3 centimeters—some of which displayed irregular vascularization. Prompted by the suspicion of a lymphoproliferative disorder, physicians performed an excisional lymph node biopsy. Histopathological analysis definitively confirmed classical Hodgkin lymphoma, nodular sclerosis subtype (Grade 1 according to British National Lymphoma Investigation criteria).
Staging and the Incidental Discovery
Following her histological diagnosis, the patient underwent a staging positron emission tomography-computed tomography (PET-CT) scan. The imaging demonstrated hypermetabolism across multiple supradiaphragmatic lymph node groups, classifying her disease as stage IIB.
Crucially, the PET-CT scan also revealed an unexpected focal increase in fluorodeoxyglucose (FDG) uptake within the right pericardiac region. This finding immediately raised clinical concerns regarding possible direct cardiac or pericardiac disease involvement. In anticipation of systemic chemotherapy, a peripherally inserted central catheter (PICC) was placed, and a total-body CT scan was performed to solidify staging metrics.
Thirteen days post-PICC placement, and prior to the administration of any chemotherapy, a routine transthoracic echocardiography (TTE) was performed. The scan uncovered a multilobulated, isoechoic mass measuring $3.5 times 2.4text cm$. Adhering firmly to the lateral wall of the right atrium and extending toward the tricuspid valve plane, the mass exhibited no overt signs of vena cava inflow obstruction or acute hemodynamic compromise.
Diagnostic Delineation and Anticoagulation Strategy
The discovery of a right atrial mass in a newly diagnosed lymphoma patient presented a profound diagnostic dilemma. Clinicians had to determine whether the mass represented a direct neoplastic invasion of the heart, a vegetation, or an incidental/catheter-related thrombus.
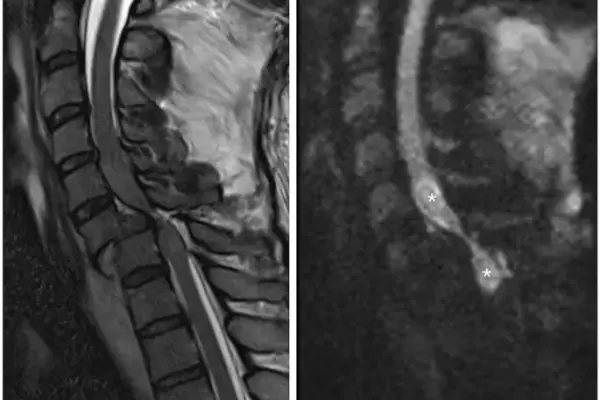
Initiating defensive measures immediately, the medical team prescribed low-molecular-weight heparin at an initial daily dose of 6,000 IU. To achieve definitive characterization without exposing the patient to invasive surgical biopsies, cardiac magnetic resonance imaging (CMR) was deployed. The CMR scan provided decisive clarity: the mass displayed isointense signals on cine, T1-weighted, and T2-weighted sequences, internal signal heterogeneity, and a total absence of both first-pass perfusion and late gadolinium enhancement. These profiles confirmed the lesion was avascular—firmly supporting a thrombotic nature rather than lymphomatous myocardial infiltration.
With the thrombotic diagnosis secured, the heparin regimen was scaled up to a full therapeutic dose of 8,000 IU twice daily. Following specialized clinical consultations, her anticoagulation therapy was transitioned to apixaban at 5 mg twice daily, which she maintained throughout her cancer treatment.
Oncologic Treatment and Follow-Up
Cleared of cardiovascular contraindications, the patient commenced systemic therapy aligned with the rigorous HD17 clinical trial regimen. This protocol consisted of two cycles of escalated BEACOPP (bleomycin, etoposide, doxorubicin, cyclophosphamide, vincristine, procarbazine, and prednisone), followed by two cycles of ABVD (doxorubicin, bleomycin, vinblastine, and dacarbazine).
The patient navigated the aggressive chemotherapeutic course remarkably well, completing all planned cycles without experiencing treatment-related toxicities, major bleeding events, or secondary thromboembolic episodes. An end-of-treatment PET-CT scan confirmed an exceptional therapeutic victory, revealing a complete metabolic response with a Deauville score of 2.
Furthermore, a follow-up TTE performed one month after the cessation of chemotherapy demonstrated a profound regression of the intracardiac mass, which had shrunk down to $1.7 times 1.2text cm$ while remaining non-obstructive to venous inflow. Subsequent outpatient follow-ups have recorded no disease relapse or secondary clinical complications.
Supporting Context & Metrics
The Mechanics of Cancer-Associated Thrombosis
Venous thromboembolism (VTE) is a notorious hallmark of oncologic pathologies, driven by a complex interplay between tumor-induced hypercoagulability, systemic inflammation, local endothelial dysfunction, and extrinsic therapeutic triggers. While the overall incidence of VTE in lymphoma patients typically ranges from 4% to 10%—escalating significantly in advanced disease stages and intensive regimens—thrombi occurring prior to the initiation of systemic therapy are exceptionally rare.
Deep vein thrombosis (DVT) and pulmonary embolism (PE) constitute the vast majority of cancer-associated clotting events. Atypical manifestations involving the cerebral venous sinuses, splanchnic veins, or cardiac chambers represent a minute fraction of cases. Right atrial thrombosis, specifically, carries an unacceptably high mortality rate if left unrecognized or untreated due to the risks of pulmonary embolism, valvular obstruction, and sudden cardiovascular collapse.
Assessing the PICC Factor
The temporal proximity between the placement of the PICC line (13 days prior to TTE detection) and the discovery of the right atrial mass introduces an essential pathophysiological variable. Central venous access devices are well-known catalysts for thrombosis. They induce local endothelial micro-trauma during insertion, alter baseline blood flow dynamics, and expose foreign surfaces that trigger the rapid activation of the coagulation cascade.
In a patient with underlying classical Hodgkin lymphoma—a condition already characterized by a pro-thrombotic systemic state—the threshold for catheter-associated thrombus formation is precipitously lowered. Because baseline cardiac imaging prior to PICC insertion was not performed, clinicians could not definitively parse whether a microscopic thrombus was already forming due to the lymphoma itself or if the PICC line served as the primary nidus. Regardless, the intersection of these two risk factors created a perfect storm for rapid thrombus accretion.
Multimodality Imaging: The Diagnostic Pivot
The case underscores the indispensability of multimodality imaging in modern hematology:
- Transthoracic Echocardiography (TTE): Serves as the crucial first-line screening tool, enabling rapid detection of intracardiac masses and immediate hemodynamic risk assessment.
- Positron Emission Tomography-Computed Tomography (PET-CT): Highly sensitive for mapping malignant metabolic activity, though vulnerable to false positives in cardiac regions due to physiological variations or non-neoplastic inflammation (as initially suspected with the pericardiac FDG uptake).
- Cardiac Magnetic Resonance (CMR): The gold standard for definitive tissue characterization. Its ability to assess perfusion, late gadolinium enhancement, and signal intensity profiles allows clinicians to definitively distinguish avascular thrombi from vascularized tumors.
Pharmacological Considerations: Navigating Drug-Drug Interactions
Managing anticoagulation in patients undergoing active chemotherapy requires sophisticated pharmacovigilance. A critical learning point from this case involves the intersection of direct oral anticoagulants (DOACs) and chemotherapeutic agents. Specifically, doxorubicin—a core component of both the BEACOPP and ABVD regimens—has been shown to alter the area under the curve (AUC) of apixaban, potentially compromising its systemic exposure and anticoagulant efficacy.
By strategically bridging initial therapy with low-molecular-weight heparin before transitioning to carefully monitored apixaban, the clinical team insulated the patient against both thrombotic progression and chemotherapy-induced pharmacokinetic failures.
Official Statements and Academic Context
The publication of this case in Frontiers in Hematology (DOI: 10.3389/frhem.2026.1874214) represents a collaborative effort by a multidisciplinary team affiliated with the Hematology Unit and associated departments at Padua University Hospital. The investigative team was spearheaded by corresponding author Dr. Andrea Visentin alongside lead author Alessandro Giordano, with contributions from specialized clinicians across hematology, cardiology, and radiology.
Reflecting on the rarity of the presentation, the authors noted in their discussion:
"Intracardiac thrombosis represents a rare and diagnostically challenging manifestation. This case highlights the importance of multimodality imaging in the differential diagnosis of right atrial masses in patients with lymphoma and underscores the need to consider both malignancy-related hypercoagulability and catheter-associated mechanisms."
Comparative Analysis of Reported Cases
To contextualize the rarity of this finding, the study authors compiled a review of documented intracardiac thrombotic events specifically associated with Hodgkin lymphoma:
| Author & Year | Patient Demographics | Type of VTE | Timing of Detection | Primary Treatment | Anticoagulation Protocol | Clinical Outcome |
|---|---|---|---|---|---|---|
| Bangolo A. et al. | 31-year-old Female | Right atrial thrombosis | 7 years post-treatment | Thrombectomy + Anticoagulation | Apixaban | Full Recovery |
| Ren S. et al. | 29-year-old Female | Right atrial thrombosis | During chemotherapy | Anticoagulation | LMWH, Apixaban | Full Recovery |
| Chan T.S. et al. | 33-year-old Female | LV thrombosis w/ endocarditis | During chemotherapy | Mitral valve replacement | Not Available | Full Recovery |
| Chan A. et al. | 56-year-old Male | Right atrial thrombosis | Post-chemotherapy | Anticoagulation / Thrombectomy eval | Heparin (NOS) | Mortality |
| Current Work (2026) | 21-year-old Female | Right atrial thrombosis | At initial diagnosis (Pre-Tx) | Systemic Anticoagulation | LMWH, Apixaban | Full Recovery |
This comparative matrix highlights that while previous cardiac thromboses in Hodgkin lymphoma predominantly manifest during or long after treatment completion, Giordano et al. document a unique clinical scenario: the identification of an atrial thrombus prior to systemic therapy in an early-stage patient.
Institutional Support and Funding
This clinical investigation and subsequent publication were made possible through competitive research grants and institutional backing. Primary financial support was provided by the Italian Association for Cancer Research (AIRC Grant IG-25024 to LT), the Italian Ministry of University and Research via PRIN PNRR (Grant P2022PSMX4 to AV), the Padua-based non-profit organization ONLUS “Ricerca per Credere nella Vita” (RCV), and the “Supporting Talent in ReSearch@University of Padua – Starting Grant Be_CL3VER” awarded to AV.
The authors formally declared that the research was conducted free of any commercial or financial conflicts of interest, ensuring unbiased academic rigor.
Future Outlook
The successful management of this complex case establishes several forward-looking paradigms for hematology-oncology practices worldwide:
- Heightened Vigilance at Staging: Clinicians are urged to maintain a heightened index of suspicion for atypical thrombotic events during the baseline work-up of hematologic malignancies. The assumption that clots only form during active chemotherapy or late-stage disease is demonstrably flawed.
- Protocolized Pre-Treatment Screening: Given the rising utilization of central venous access devices (such as PICC and Hickman lines) immediately following lymphoma diagnosis, cardiovascular imaging protocols should carefully evaluate right-sided heart chambers to establish baseline vascular integrity before systemic therapies begin.
- Advanced Pharmacological Tailoring: As DOACs become increasingly preferred in cancer-associated thrombosis, oncologists must remain vigilant regarding complex pharmacokinetic interactions with cytotoxic drugs like doxorubicin. Multidisciplinary collaboration between hematologists, cardiologists, and clinical pharmacologists will remain essential to optimize dosing schedules.
- Informed Prospective Registries: Because data regarding right atrial thrombosis in classical Hodgkin lymphoma largely remains restricted to isolated case reports and small retrospective series, larger prospective multicenter registries are needed to establish standardized guidelines for managing pre-treatment intracardiac thrombi without compromising curative cancer regimens.
Ultimately, the case of this 21-year-old patient proves that even in the face of daunting, overlapping vascular and oncologic complications, rapid diagnostic clarity and synchronized medical therapy can steer patients away from catastrophe and toward complete, long-term remission.